Generic Hydrocodone m367
Price range: $538.00 through $1,514.00
| Variation | Price | Quantity | Add To Cart |
|---|---|---|---|
| 360 pills | $1,514.00 |
|
Add to cart |
| 180 pills | $913.00 |
|
Add to cart |
| 90 pills | $538.00 |
|
Add to cart |
M367 Pill: Hydrocodone 10 mg/Acetaminophen 325 mg Safety and Prescription Guide
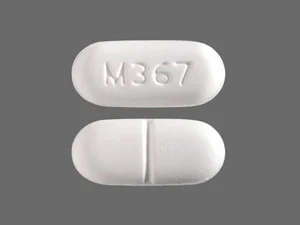
M367 is the imprint used on a white, capsule-shaped prescription tablet that contains hydrocodone bitartrate 10 mg and acetaminophen 325 mg in current U.S. DailyMed labeling. The opposite side is bisected. Hydrocodone is a potent opioid analgesic, while acetaminophen is a non-opioid pain reliever. The combination may be prescribed for pain severe enough to require an opioid when non-opioid or other alternatives are ineffective, not tolerated, or otherwise inadequate.
The 10 mg hydrocodone content makes M367 a higher-strength immediate-release hydrocodone/acetaminophen tablet than M365, which contains hydrocodone 5 mg with the same 325 mg of acetaminophen. The imprint is not a dose instruction, and a score line does not authorize a patient to split or adjust the tablet without pharmacy or prescriber guidance.
Hydrocodone combination products are Schedule II controlled substances in the United States. They can cause addiction, misuse, physical dependence, life-threatening respiratory depression, overdose, and death. M367 should be used only by the patient named on a valid prescription and obtained from a licensed pharmacy. This page is not an offer to supply hydrocodone without a prescription.
Verified M367 Profile
- Imprint: M367.
- Hydrocodone strength: 10 mg per tablet.
- Acetaminophen strength: 325 mg per tablet.
- Appearance in the referenced label: white, capsule-shaped, M367 on one side and bisected on the other.
- Dosage form: immediate-release oral combination tablet.
- U.S. status: prescription only; Schedule II controlled substance.
- Primary safety priorities: prevent respiratory depression, sedative combinations, acetaminophen overdose, diversion, and counterfeit exposure.
A pill finder or imprint page can help form a question for a pharmacist, but it cannot authenticate a tablet. Counterfeit pills may copy “M367” while containing illicit fentanyl or another unexpected substance. Do not swallow any loose, found, shared, street-purchased, or unverified online pill.
Why the 10 mg Hydrocodone Strength Requires Respect
Milligrams cannot be interpreted without opioid tolerance, age, organ function, respiratory health, and other medicines. A 10 mg hydrocodone tablet can cause serious respiratory depression in an opioid-naive or medically vulnerable person. A dose that was previously tolerated may become unsafe after a break because tolerance can decline.
The risk also changes when a sedative, benzodiazepine, gabapentinoid, alcohol, muscle relaxant, sleeping medicine, or CYP3A4 inhibitor is added. A patient should never judge safety by comparing M367 with another person’s prescription or by recalling a dose used months ago.
The prescriber should use the lowest effective opioid dose for the shortest time consistent with the clinical need. If pain is uncontrolled, the answer is reassessment, not an extra tablet. Worsening pain can reflect a complication, disease progression, tolerance, or opioid-induced hyperalgesia.
M367 Versus M365: Do Not Substitute by Imprint
| Feature | M365 | M367 |
|---|---|---|
| Hydrocodone | 5 mg | 10 mg |
| Acetaminophen | 325 mg | 325 mg |
| Relative hydrocodone amount | Reference strength | Twice the hydrocodone per tablet |
| Control status | Schedule II | Schedule II |
| Can one replace the other? | No substitution or conversion should occur without the prescriber and pharmacist. | |
The shared 325 mg acetaminophen amount can make the tablets look more similar on a medication list than they are clinically. Accidentally taking M367 according to directions intended for M365 can double hydrocodone exposure per tablet. Check the bottle and imprint at every fill.
Other manufacturers use different imprints for hydrocodone 10 mg/acetaminophen 325 mg. A different imprint is not automatically wrong, but it should be confirmed by the dispensing pharmacist. Never select a tablet based only on color or shape.
What Pain Situations May Lead to a Prescription
Hydrocodone/acetaminophen labeling limits use to pain severe enough to require an opioid and for which alternatives are inadequate. This can include selected short-term pain after surgery, injury, or a procedure, and certain other pain conditions evaluated by a clinician. The higher tablet strength does not mean it is suitable for every case described as “severe.”
The prescriber should consider non-opioid medication, local treatment, ice or heat when appropriate, physical therapy, immobilization, behavioral approaches, or a procedure depending on the cause. Some pain conditions respond poorly to opioids or become more complicated with long-term use.
A useful prescription has a defined goal. Examples include tolerating wound care, sleeping for a safe recovery period, walking enough to prevent complications, or participating in rehabilitation. If the medicine does not improve the intended function, ongoing exposure may not be justified.
Prescription Label Verification Before the First Dose
- Confirm that the bottle shows the correct patient name.
- Confirm hydrocodone 10 mg and acetaminophen 325 mg.
- Compare the tablet imprint with the pharmacy label and supplied information.
- Read the exact number of tablets per dose, interval, maximum amount, and duration.
- Review every warning sticker and the medication guide.
- Check whether another current medicine contains acetaminophen or causes sedation.
- Ask how to obtain and use an opioid overdose reversal medicine.
- Know the follow-up date and what to do if pain remains severe.
If anything is unclear, do not take the tablet until the dispensing pharmacist explains it. Do not use an old instruction from a previous prescription or a dosage found online. “Take as needed” always operates within the written maximum and interval.
Respiratory Depression: The Most Immediate Opioid Danger
Hydrocodone reduces respiratory drive. Serious, life-threatening, or fatal breathing problems can occur at any time, but risk is especially high when treatment starts, the dose increases, another respiratory depressant is added, or an opioid is resumed after tolerance has fallen.
Overdose signs include very slow, shallow, or stopped breathing; long pauses or irregular breaths; choking or gurgling; extreme sleepiness; inability to wake; limpness; pale, gray, or blue lips or skin; and pinpoint pupils. Do not assume the person is merely sleeping.
Call emergency services immediately, administer an available opioid overdose reversal product according to its directions, and stay with the person. If breathing is absent and you are trained, follow emergency-dispatch instructions. A reversal product can wear off before hydrocodone, so the person still needs emergency evaluation even after waking.
Create a Naloxone Plan Before the Prescription Is Needed
Ask the prescriber or pharmacist about naloxone or another approved opioid overdose reversal medicine. A plan is particularly important with higher opioid strength, sleep apnea or lung disease, concurrent sedatives, a history of overdose or substance use, or other household members who could ingest the medicine.
Household members should know where the reversal product is stored, how the device works, when to call emergency services, and that repeated administration may be required according to product instructions. Check the expiration date and storage conditions periodically.
Providing naloxone is a safety measure, not an accusation of misuse. Accidental dosing, unexpected sensitivity, drug interaction, or counterfeit exposure can affect people without an opioid use disorder.
Do Not Combine M367 With Alcohol or Unapproved Sedatives
Benzodiazepines, alcohol, other opioids, sleeping pills, muscle relaxants, gabapentin, pregabalin, sedating antihistamines, antipsychotics, and recreational depressants can intensify sedation and respiratory depression. The result can be coma or death.
Tell the hydrocodone prescriber about every sedating product, even if it is taken only at night or occasionally. Tell other clinicians and dentists about the hydrocodone prescription before a sedative or procedure medicine is added. Do not stagger the drugs based on an internet interval and assume the interaction is gone.
Alcohol also complicates acetaminophen safety and judgment. Do not drink while using M367 unless a clinician who understands your full health history has given explicit advice. Never use alcohol to increase pain relief or help with sleep.
Acetaminophen: The Second Overdose Risk
M367 contains 325 mg of acetaminophen per tablet. Additional acetaminophen may be present in cold, cough, migraine, arthritis, sleep, dental, and prescription pain products. The abbreviation APAP also means acetaminophen.
Severe liver injury can occur when too much acetaminophen is taken. The total must include every source in the same 24-hour period. Although many U.S. materials identify 4,000 mg per day as a general adult ceiling, an individual limit may be lower and the prescribed M367 maximum is controlling. Liver disease, alcohol use, fasting, malnutrition, age, and other factors can change risk.
Do not perform tablet calculations to see how many M367 pills fit under a general acetaminophen ceiling. Hydrocodone toxicity may occur well before that number, and the prescription may set a much lower maximum. If excess acetaminophen may have been taken, seek urgent professional guidance even without symptoms.
Medication Interactions That Can Raise Hydrocodone Exposure
Hydrocodone metabolism involves CYP3A4 and CYP2D6. CYP3A4 inhibitors—including some macrolide antibiotics, azole antifungals, and protease inhibitors—can increase or prolong hydrocodone effects and respiratory risk. Effects may be greater when CYP3A4 and CYP2D6 inhibitors are both involved.
CYP3A4 inducers can lower hydrocodone concentrations. Stopping an inducer may then allow levels to rise. Adding or stopping either type of medicine requires clinical monitoring; the patient should not compensate by changing the M367 dose.
Monoamine oxidase inhibitors, serotonergic medicines, mixed agonist/antagonist opioids, partial agonists, anticholinergic drugs, and diuretics can create other clinically important problems. Provide the pharmacist with the actual list rather than relying on a partial internet checker.
Conditions That Increase Risk
Tell the prescriber about asthma, COPD, sleep apnea, reduced breathing reserve, recent respiratory infection, head injury, brain tumor, seizures, low blood pressure, bowel obstruction, gallbladder or pancreatic disease, liver or kidney impairment, thyroid disease, adrenal insufficiency, prostate enlargement, or urinary difficulty.
Hydrocodone/acetaminophen is contraindicated in significant respiratory depression, acute or severe bronchial asthma in an unmonitored setting or without resuscitative equipment, known or suspected gastrointestinal obstruction including paralytic ileus, and hypersensitivity to an ingredient.
Older adults may be more sensitive to opioid respiratory and sedating effects. Frailty, falls, cognitive impairment, and multiple medicines increase complexity. Lower starting exposure and closer monitoring may be required; a 10 mg tablet should not be selected merely for convenience.
Pregnancy, Fertility, and Breastfeeding
Prolonged opioid use during pregnancy can cause neonatal opioid withdrawal syndrome, which may be life-threatening if not recognized and treated. Tell the prescriber immediately about pregnancy or plans to become pregnant. Do not stop regular opioid therapy suddenly without guidance.
Hydrocodone passes into breast milk. An exposed infant may develop excess sleepiness, difficulty feeding, limpness, or breathing problems. The patient and clinician must weigh the clinical need, alternatives, and infant risk. Seek immediate care if an infant has abnormal sleepiness or breathing.
Long-term opioid use can affect endocrine function and fertility in some patients. Report changes in libido, menstrual pattern, erectile function, or unexplained fatigue during ongoing therapy.
Expected Effects, Common Side Effects, and Red Flags
Sleepiness, dizziness, lightheadedness, nausea, vomiting, and constipation are common. Some patients experience itching or sweating. These effects can interfere with driving, work, balance, and safe childcare.
Do not drive, operate machinery, climb, swim alone, or perform another hazardous activity until you know the response and the prescriber says it is appropriate. Sitting or lying down may help reduce injury if lightheadedness occurs, but fainting or severe hypotension requires prompt assessment.
Emergency concerns include slow or difficult breathing, inability to wake, severe confusion, fainting, severe allergic symptoms, and suspected overdose. Prompt medical review is also needed for yellow skin or eyes, dark urine, persistent upper abdominal pain, a severe skin reaction, or signs of bowel obstruction.
Constipation Is Predictable and Should Be Planned For
Opioid constipation may begin with the first doses and does not always improve over time. Ask the clinician or pharmacist whether a preventive bowel regimen is appropriate. Fluid, fiber, and activity advice must account for kidney, heart, bowel, and mobility conditions.
Track bowel movements, abdominal discomfort, nausea, and appetite. Severe or increasing abdominal pain, vomiting, marked swelling, or inability to pass stool or gas may signal a serious problem. Do not keep adding laxatives if obstruction is possible.
Constipation management is part of opioid safety, not a minor comfort issue. A patient who avoids the medicine because of constipation or takes extra medicine after vomiting needs a revised plan.
Dependence, Withdrawal, and Tapering
Physical dependence can develop with regular opioid use. Abrupt discontinuation may cause restlessness, sweating, runny nose, yawning, muscle aches, abdominal cramps, diarrhea, insomnia, anxiety, increased pain, and other symptoms. Physical dependence is not identical to addiction, but it requires a safe discontinuation plan.
Do not rapidly reduce or stop M367 after regular use without the prescriber. A taper should consider current dose, duration, pain condition, withdrawal response, mental health, and the patient’s goals. Randomly skipping doses or cutting tablets without approval creates unstable exposure.
Loss of tolerance after a break is critical. Returning to a previously tolerated amount can cause overdose. If treatment is interrupted, contact the prescriber before restarting.
Recognizing Possible Opioid Use Disorder
Warning patterns include taking more or taking it more often than prescribed, using hydrocodone for anxiety or sleep rather than pain, craving, hiding use, repeated early refill requests, obtaining pills from multiple sources, continued use despite harm, or inability to cut down.
These signs require prompt, compassionate medical help. Do not punish the patient by abruptly taking away medication or leave them to manage withdrawal alone. Effective treatment for opioid use disorder exists, and a qualified clinician can help choose the next step.
Family members should focus on immediate safety, honest communication, secure storage, and professional care. A reversal medicine should remain available.
A Daily Monitoring Record for Short-Term Therapy
A simple written record can prevent dosing mistakes and improve follow-up. Record the date, time taken, prescribed amount, pain-related activity goal, effect on function, sleepiness, breathing concerns, nausea, bowel movement, and remaining tablet count. Do not include extra doses outside the prescription.
Review the record with the prescriber if therapy continues. It can reveal that pain is improving and fewer doses are needed, that side effects outweigh benefit, or that a complication is causing worsening pain.
Keep the record private and separate from the bottle so it does not advertise where the controlled medicine is stored. Caregivers involved in dosing should use one shared record to prevent duplicate administration.
Filling an M367 Prescription Through a Licensed Pharmacy
Searches such as “M367 prescription pharmacy,” “fill hydrocodone 10/325 prescription,” or “hydrocodone acetaminophen pharmacy availability” should lead to lawful dispensing, not an anonymous product order. The pharmacy must receive a valid controlled-substance prescription and be appropriately licensed and registered.
FDA guidance for online pharmacies recommends verifying that the pharmacy requires a prescription, lists a U.S. address and telephone number, provides a licensed pharmacist, and is licensed by the state board of pharmacy. Patients should independently check the license rather than trust a displayed badge.
A controlled-substance prescription may involve identity checks, prescriber verification, insurance review, monitoring-program review, stock limitations, and legal restrictions on transfers or shipping. A seller offering to avoid all checks is not providing a safer convenience.
Price, Insurance, and Availability Questions
Ask a licensed pharmacy for the final cost of the exact prescribed quantity and manufacturer. Insurance deductibles, formularies, quantity limits, and pharmacy networks can affect price. Discount cards may have controlled-substance restrictions.
Do not search for a bulk pack or choose a higher quantity because the unit price seems lower. The smallest clinically appropriate quantity reduces unused tablets and diversion risk. If the pharmacy cannot fill the prescription, contact the prescriber and pharmacist about permitted transfer or an appropriate alternative.
Never respond to “cheap M367 no prescription,” “worldwide hydrocodone shipping,” or social-media offers. No price advantage offsets the risk of counterfeit fentanyl, unlawful supply, or fatal overdose.
Counterfeit M367 Pills and Fentanyl Risk
Illicit manufacturers can press counterfeit tablets that resemble legitimate prescription opioids. The imprint, white color, capsule shape, and score line can all be copied. A pill’s appearance cannot show whether it contains hydrocodone, fentanyl, another substance, or an unpredictable dose.
The safest rule is source-based: only use medicine dispensed for you by a licensed pharmacy. Do not buy through a messaging app, street source, online marketplace, social media, or a website that ships without a prescription. Do not accept a pill from a friend or relative.
If a licensed-pharmacy refill looks unexpected, do not take it until the pharmacist verifies the product. Keep it in the labeled container. Report damaged packaging, a missing seal, misspelled labeling, or an unexplained change.
Secure Storage and Inventory Control
Keep M367 locked, out of sight, and inaccessible to children, teenagers, visitors, and anyone at risk of misuse. Store it in the original patient-labeled, child-resistant container and follow the temperature and light instructions on the label.
Count the tablets when received and during therapy. Investigate missing tablets promptly without placing anyone in danger. Do not leave doses on a counter, in a handbag, in a vehicle, or in an unlocked bedside drawer.
Accidental ingestion of one tablet can be fatal to a child or opioid-naive adult. Never share M367, even when another person has severe pain.
Disposal When Treatment Ends
Dispose of leftover tablets promptly through an authorized drug take-back program or DEA-registered collector when available. Follow the medication guide supplied with the exact product and local pharmacist instructions for alternatives when take-back is not readily available.
Do not retain M367 for future injuries, sell it, give it to another person, or discard it where someone can retrieve it. Remove personal information from an empty bottle only after the medication is no longer needed and relevant pharmacy questions are resolved.
Questions to Resolve Before Leaving the Pharmacy
- Does this tablet contain hydrocodone 10 mg and acetaminophen 325 mg?
- How does this prescription differ from any previous hydrocodone strength?
- Which exact medicines and substances must I avoid?
- How much total acetaminophen am I permitted from all products?
- What is my constipation prevention plan?
- Should I keep an opioid overdose reversal medicine at home, and how is it used?
- What should I do if the medicine causes severe sleepiness or does not control pain?
- When will the prescriber reassess therapy?
- How should I dispose of unused tablets?
Refills, Early Requests, and Continuity of Care
Schedule II prescription rules differ from ordinary refill processes. Do not wait until the last tablet to clarify the treatment plan, especially before weekends, travel, or a prescriber absence. Contact the treating office and pharmacy through their normal channels and allow time for lawful review.
An early request can occur for several reasons: pain worsened, directions were misunderstood, tablets were lost, vomiting occurred, or the medicine is being used outside the plan. Explain exactly what happened. Do not change the story to obtain a replacement. The clinician needs accurate information to identify overdose risk, diversion, a surgical complication, or a developing opioid-use problem.
Never bridge a gap with a friend’s prescription, an old bottle, or an online purchase. The strength may differ, tolerance may have changed, and the tablet may be counterfeit. If regular use has created physical dependence, the prescriber can address withdrawal risk and continuity safely.
Use one prescriber and one pharmacy when possible so medication history and safety checks remain coordinated. Tell each urgent-care, dental, or specialist clinician about the opioid plan before another pain or sedating medicine is prescribed.
Longer-Term Therapy Requires a Different Standard
A medicine that is reasonable for a few days after a procedure may not remain the best choice for chronic pain. With longer use, the prescriber should reassess function, adverse effects, tolerance, dependence, mental health, overdose risk, sleep-disordered breathing, and whether non-opioid or non-drug treatment can reduce exposure.
Functional goals should be specific and observable. Examples might include walking a defined distance, completing household tasks, attending therapy, or sleeping enough to participate in rehabilitation. A lower pain score without meaningful improvement in life and function may not justify continued risk.
Monitoring may include prescription records, medication counts, toxicology testing when clinically appropriate, treatment agreements, and periodic review of the opioid-reversal plan. These practices should support safety and communication. They do not eliminate the need to listen to the patient or evaluate new pain.
If benefits no longer outweigh harms, the clinician may recommend a gradual taper or transition to another treatment. The plan should avoid abrupt discontinuation, address withdrawal and mental health, and provide follow-up. Patients should report fear, craving, or difficulty controlling use openly so care can be adjusted.
Emergency Information to Keep With the Medication
Keep a concise, current list of the patient’s medicines, allergies, diagnoses, prescriber, pharmacy, and opioid-reversal product in a location caregivers can find without exposing the controlled medicine. Include the prescribed M367 strength and the time of the most recent dose when someone is actively monitoring the patient.
Caregivers should know that loud snoring, gurgling, unusual pauses in breathing, or an inability to wake the patient is not normal sleep. They should call emergency services promptly and use the reversal medicine according to its directions. Waiting for a person to “sleep it off” can be fatal.
If emergency care occurs, bring the labeled bottle and all other medicines. Tell the team about alcohol, cannabis, benzodiazepines, sleep aids, gabapentinoids, or other substances without withholding information. The immediate goal is accurate treatment.
Why Doorstep Convenience Cannot Replace Pharmacy Counseling
Mail delivery may be lawful when performed by a properly licensed pharmacy under a valid prescription, but delivery speed is not the key measure of quality. For M367, the service should verify the prescription, patient, address, pharmacy authorization, product, and ability to provide counseling.
Confirm what happens if the package is delayed, damaged, left in an insecure place, or appears tampered with. Controlled medicine should not be exposed to theft or accessible to a child. Arrange a delivery method consistent with pharmacy requirements and household safety.
When the package arrives, check the patient label, seal, quantity, imprint, and expiration information before use. Contact the dispensing pharmacist about any discrepancy. Do not accept a replacement directly from a courier, seller, or messaging contact outside the licensed pharmacy process.
Frequently Asked Questions About M367
What is the white M367 pill?
Current DailyMed labeling identifies it as hydrocodone bitartrate 10 mg with acetaminophen 325 mg, in a white capsule-shaped tablet marked M367.
Is M367 stronger than M365?
M367 contains 10 mg of hydrocodone, while M365 contains 5 mg; both contain 325 mg acetaminophen. Do not substitute or convert them without the prescriber and pharmacist.
Is M367 Schedule II?
Yes. Hydrocodone combination products are Schedule II controlled substances in the United States.
Can an M367 tablet be split?
The referenced tablet is bisected, but a patient should split it only if the prescriber or pharmacist confirms that the exact prescription and product should be divided. A score line is not permission to self-adjust.
Can I take M367 with acetaminophen?
M367 already contains 325 mg acetaminophen. Do not add another acetaminophen product until a pharmacist or prescriber checks the total and confirms the plan.
Can I take M367 with alprazolam, diazepam, or a sleeping pill?
These combinations can cause profound sedation and life-threatening respiratory depression. Do not combine them unless the prescribers have coordinated a specific monitored plan.
What if my pain returns before the next prescribed dose?
Do not take an early or extra tablet. Contact the treating clinician to assess the pain, the diagnosis, and safer options.
Can I buy M367 online?
A legitimate pharmacy will require a valid controlled-substance prescription and must meet licensing and registration requirements. Avoid any seller offering M367 without a prescription.
How can I tell whether an M367 pill is counterfeit?
You cannot authenticate a pill by appearance alone. Only use a tablet dispensed for you in a labeled container from a verifiable licensed pharmacy.
What should I do in a suspected overdose?
Call emergency services, give an available opioid overdose reversal medicine according to its instructions, and remain with the person. Emergency evaluation is required even if the person wakes.
Final Safety Summary
M367 contains hydrocodone 10 mg and acetaminophen 325 mg. It is a higher-hydrocodone-strength tablet than M365 and must not be substituted using an old label or online conversion. Major dangers include respiratory depression, overdose, addiction, sedative interactions, counterfeit pills, and liver injury from combined acetaminophen products.
Use only the amount and timing on your own current prescription. Verify the pharmacy, count every acetaminophen source, avoid alcohol and unapproved sedatives, create an opioid-reversal plan, monitor breathing and alertness, lock the medicine after every use, and dispose of leftovers promptly.
When pain remains uncontrolled, contact the prescriber. When breathing slows, the patient cannot be awakened, or overdose is suspected, call emergency services immediately. Never use an anonymous online or street source, even if the pill appears to have the correct M367 imprint.
Medical References Reviewed
- Current U.S. DailyMed hydrocodone bitartrate and acetaminophen labeling, including the M367 strength, appearance, boxed warnings, and medication guide.
- U.S. Drug Enforcement Administration information on hydrocodone combination products and Schedule II controls.
- U.S. Food and Drug Administration BeSafeRx information for identifying a safer online pharmacy.
| Select Variation |
360 pills ,180 pills ,90 pills |
|---|